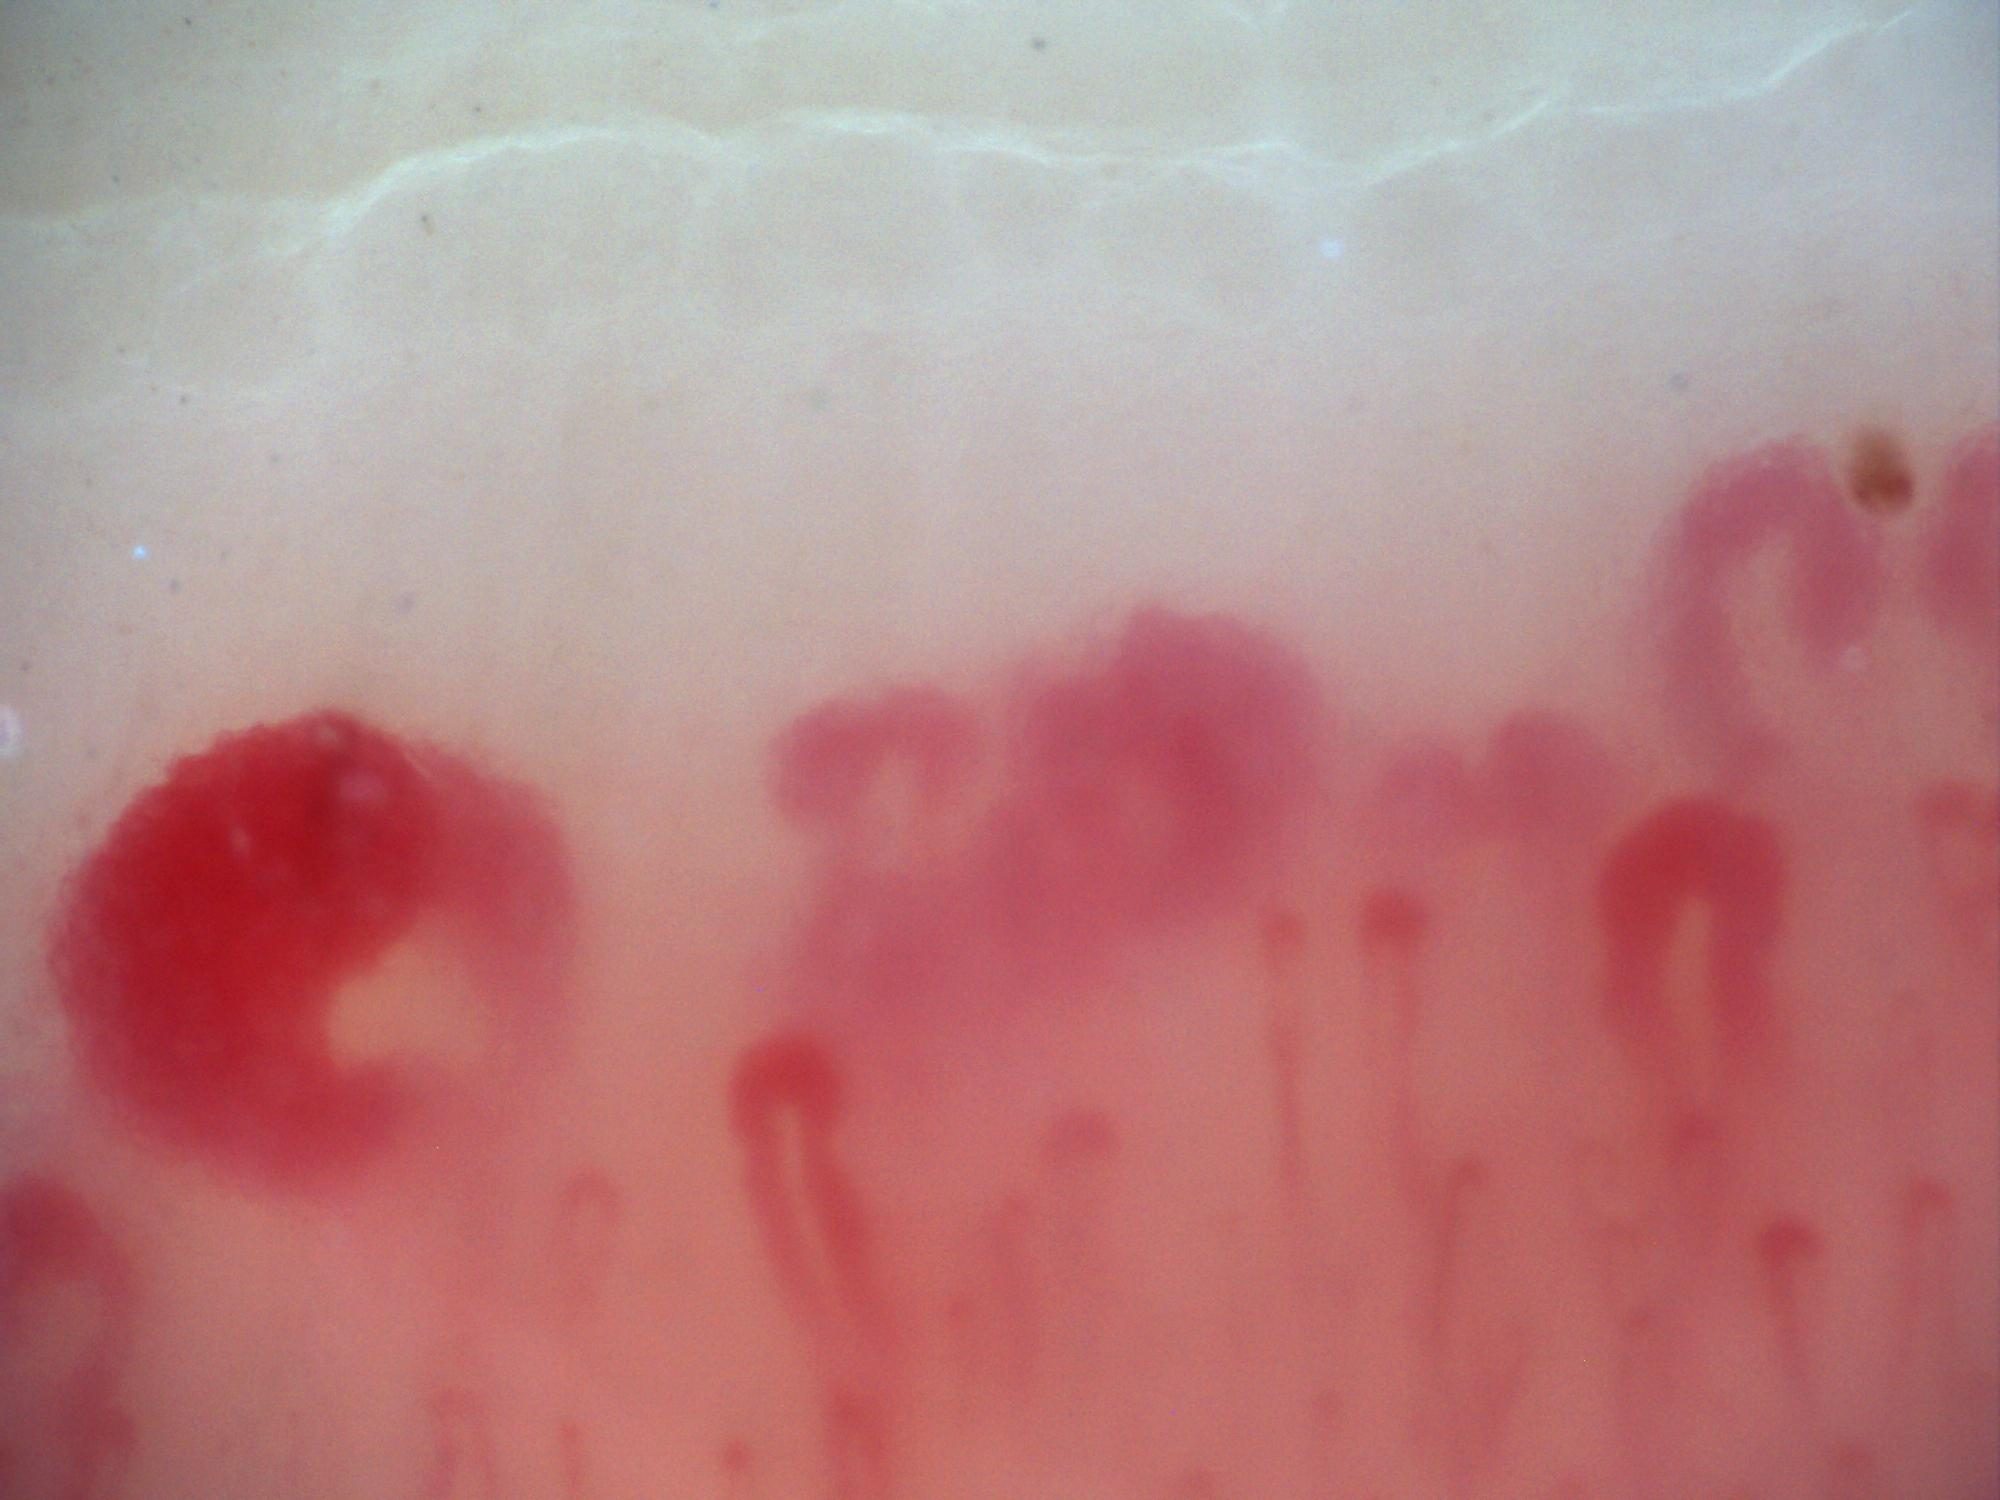
200x capillaroscopy image from systemic sclerosis showing a very large megacapillary.
How to assess and measure
Use a calibrated image to measure the apical diameter in micrometers. Record the presence and distribution of giants across assessable fingers; if reporting a proportion, state the counting method and denominator. Display magnification and digital zoom cannot substitute for calibration. The examples below have no new individual diameter measurements attached to them.
Interpretation and related diseases
Giants are an important part of scleroderma-pattern microangiopathy, especially early and active patterns. Similar findings may occur in dermatomyositis and overlap connective tissue disease. Interpret them with hemorrhages, capillary density, architecture, clinical findings and autoantibodies; they do not establish systemic sclerosis on their own.
Read the detailed clinical chapterCommon mistakes
- Calling every dilated or coiled loop a giant without measuring it.
- Assigning an active pattern from one giant capillary in one field.
- Confusing a study-wide percentage of giants with the diameter of the capillary shown.
Real images and comparisons
Captions distinguish the illustrated finding from the study interpretation. Comparisons include variants, other clinical contexts or artifacts where available.
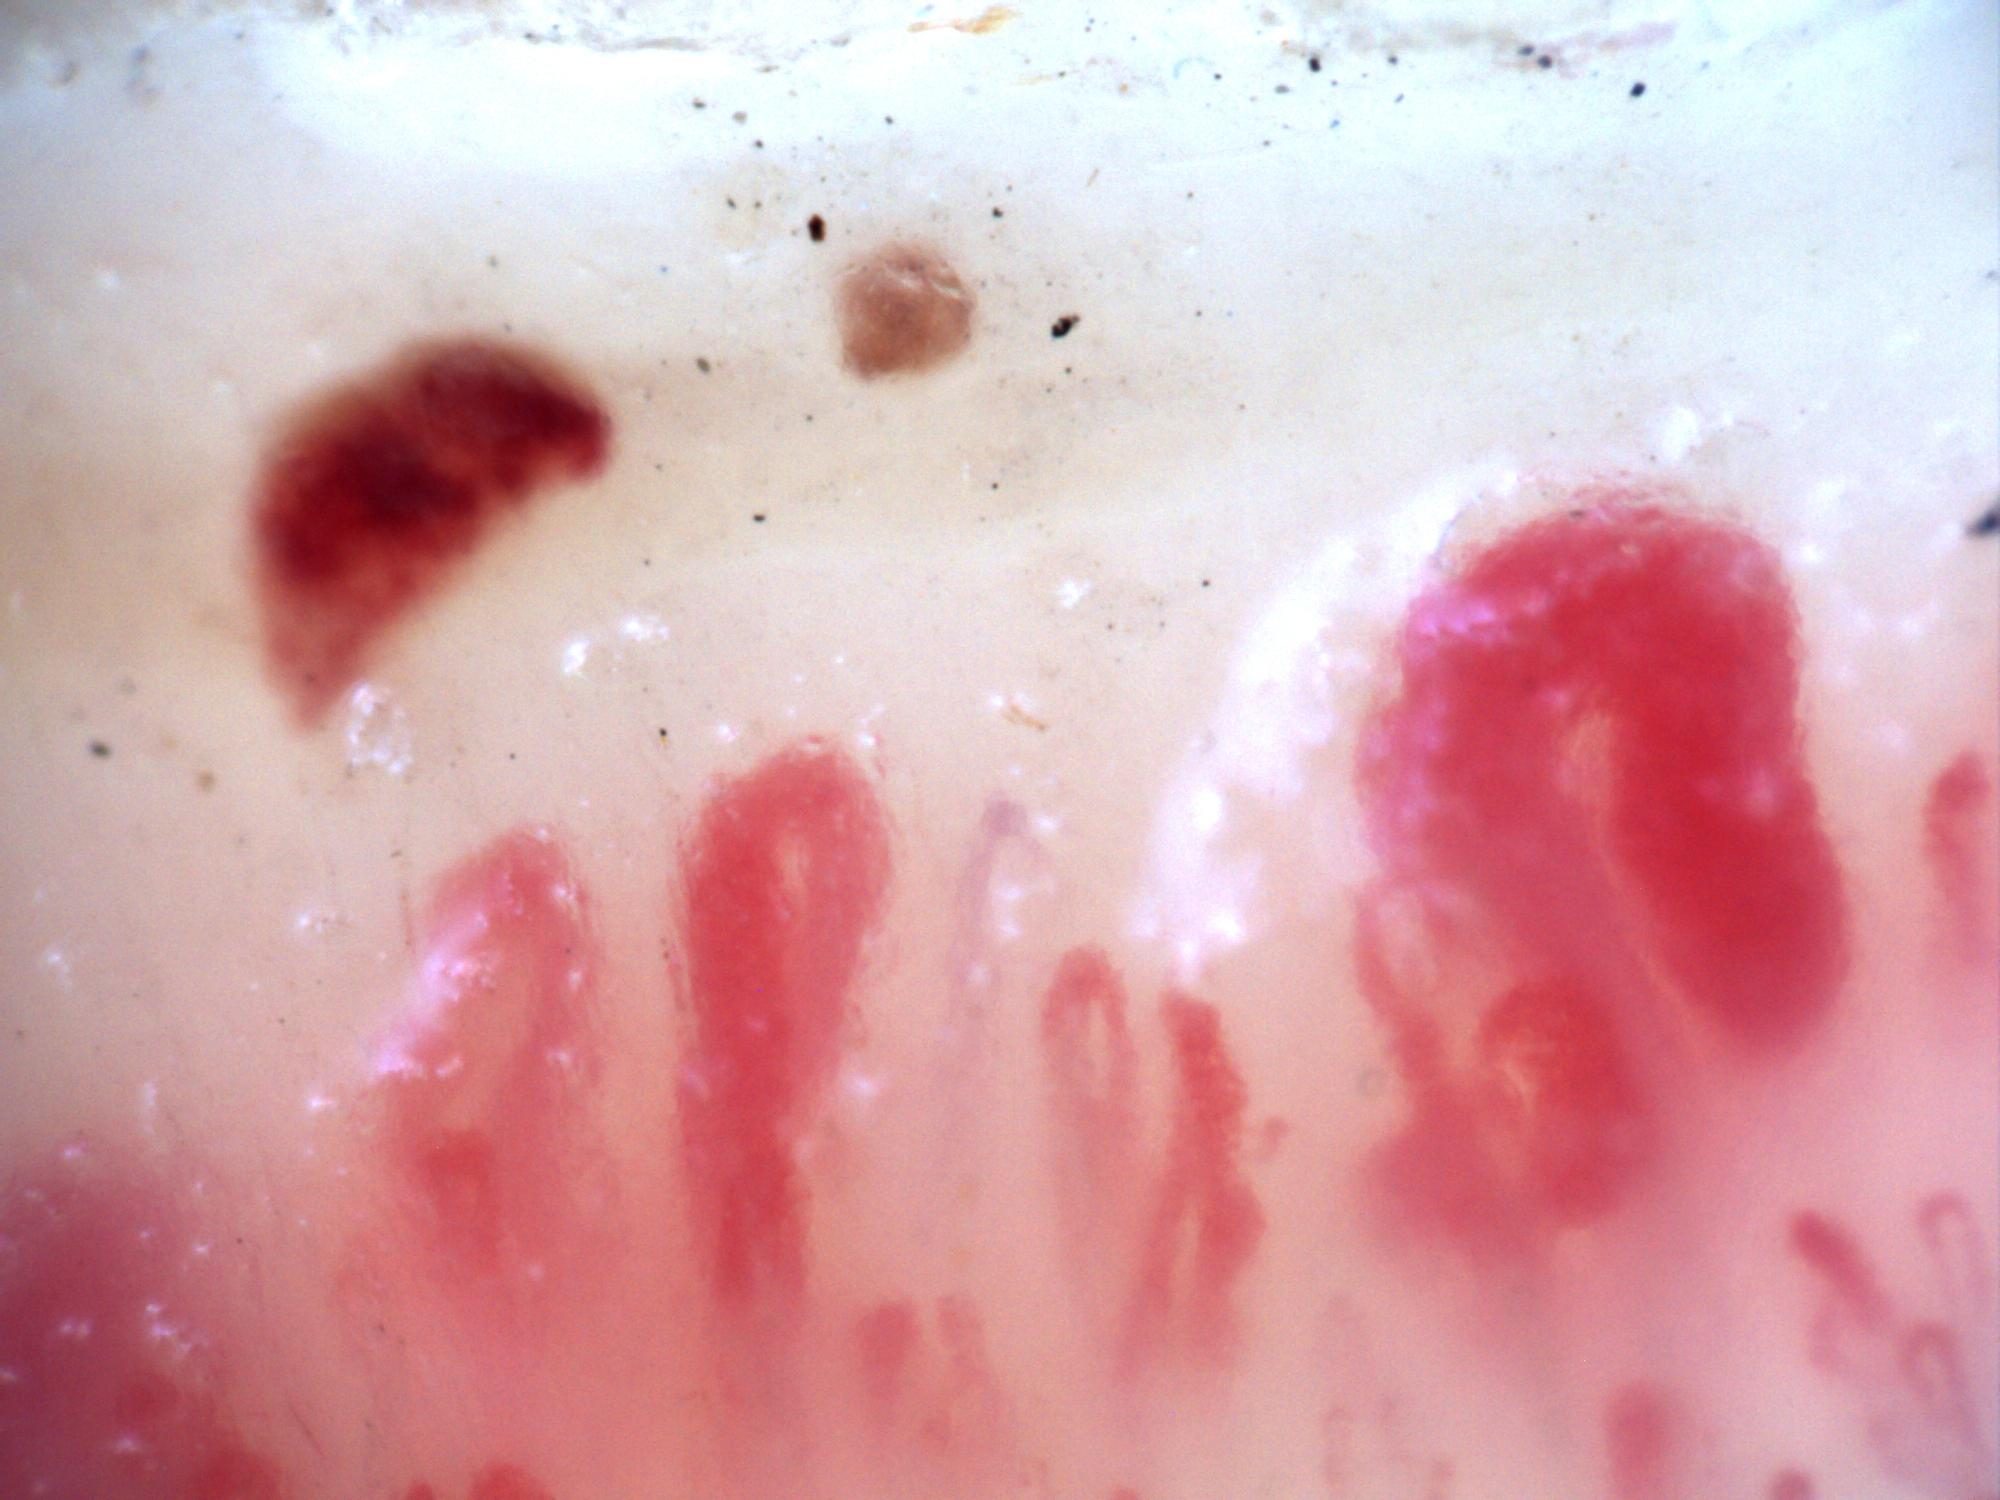
Second 200x capillaroscopy image with a large megacapillary in systemic sclerosis.
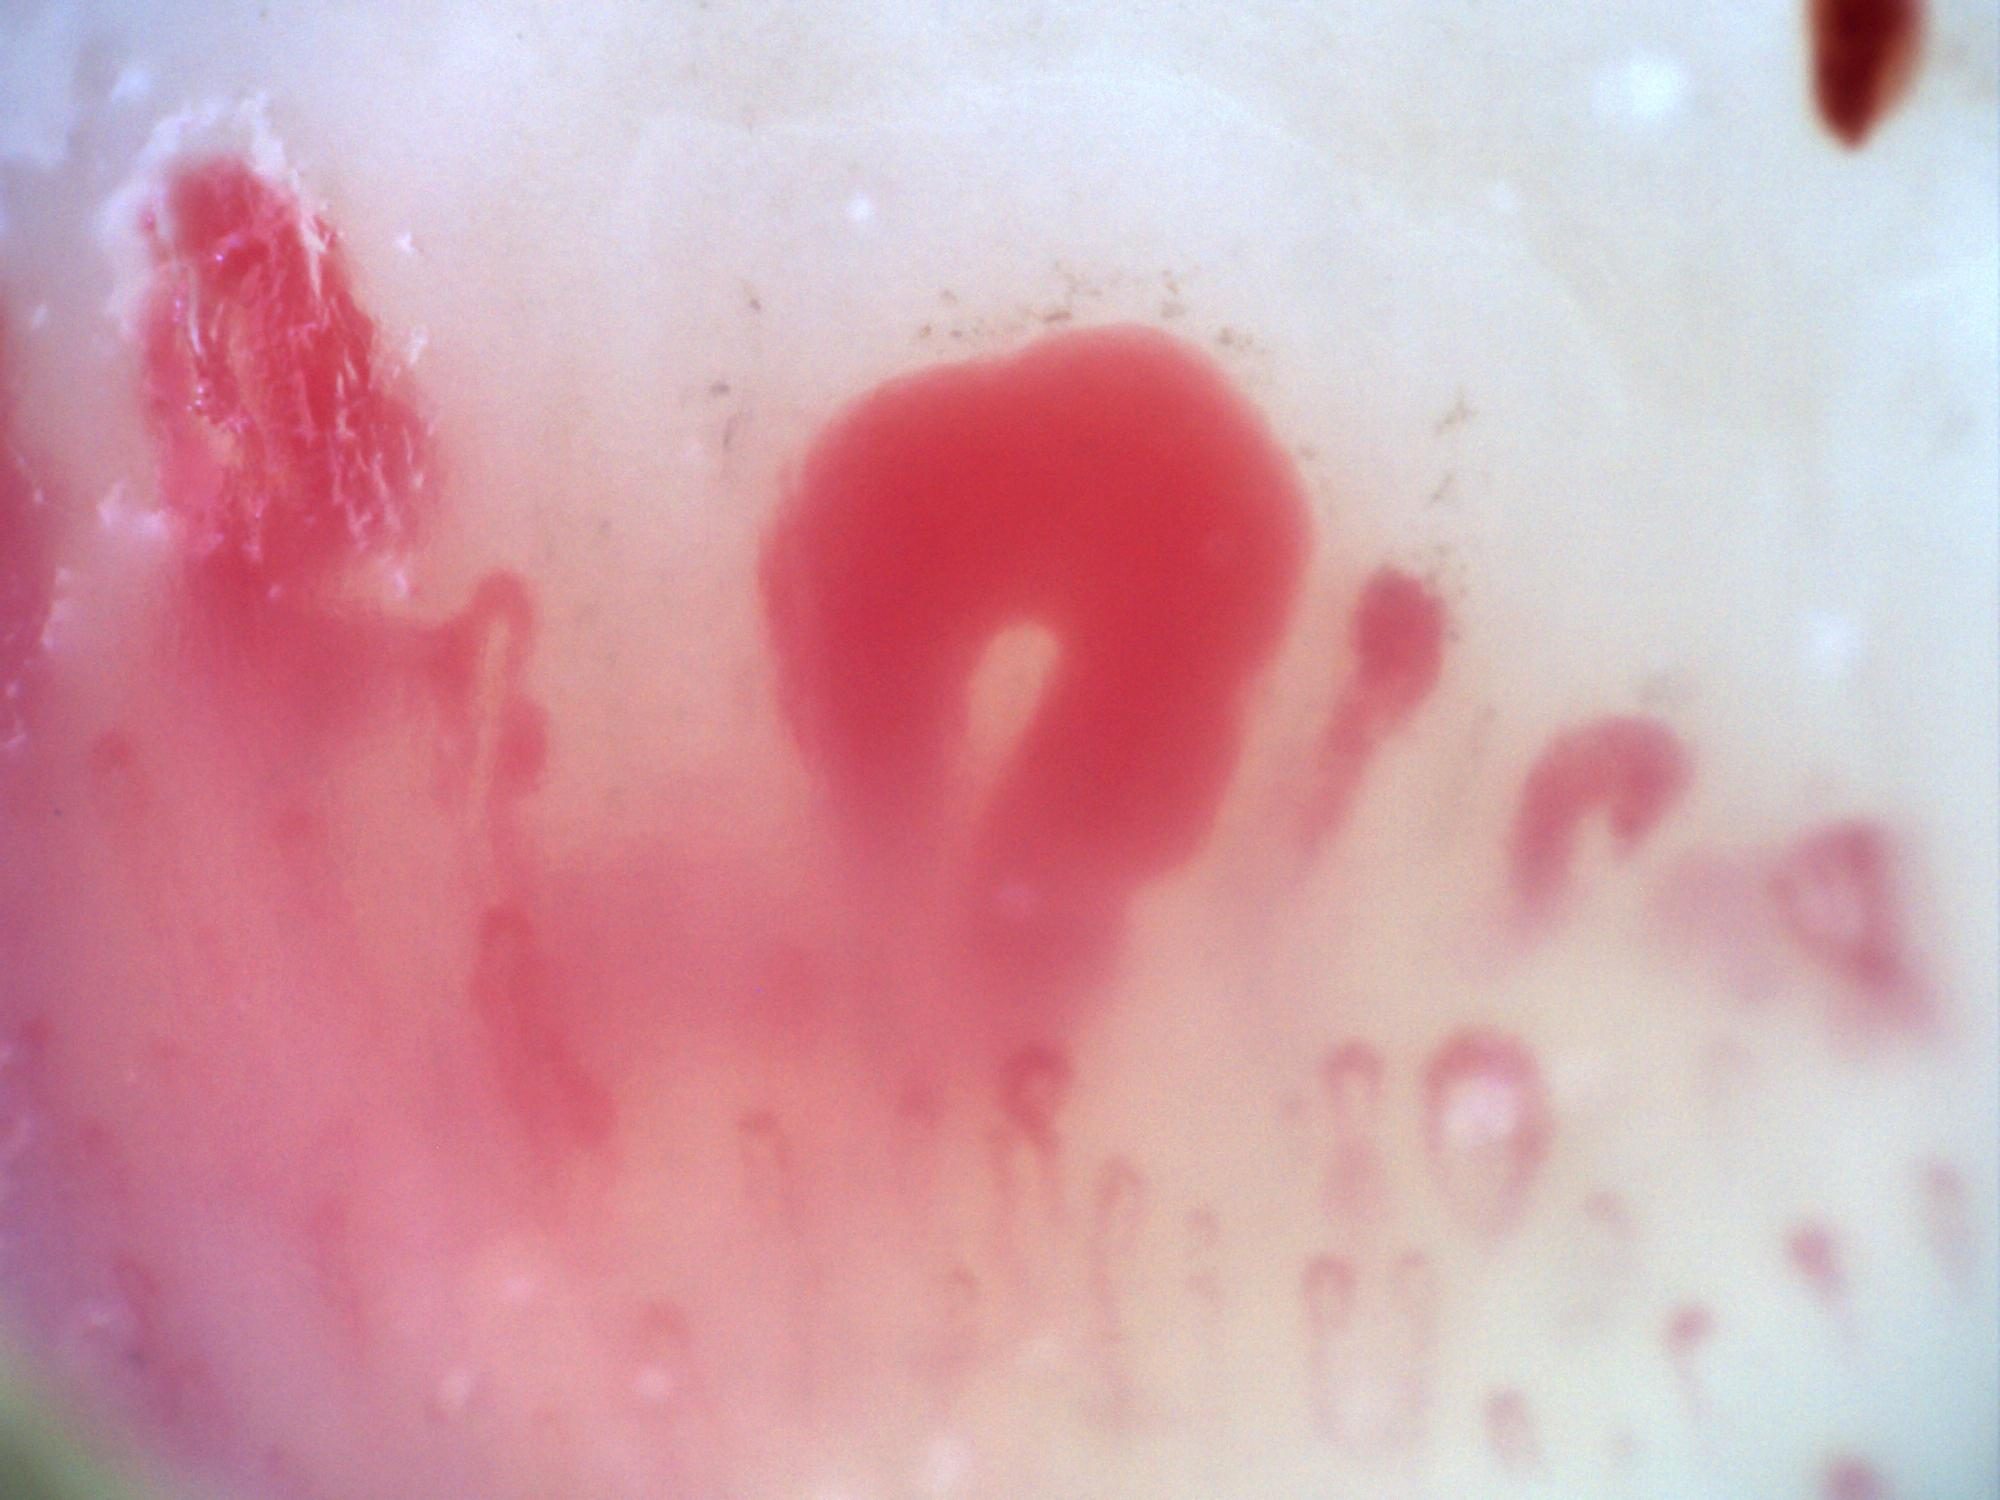
Third 200x capillaroscopy image showing large megacapillaries in a systemic sclerosis setting.
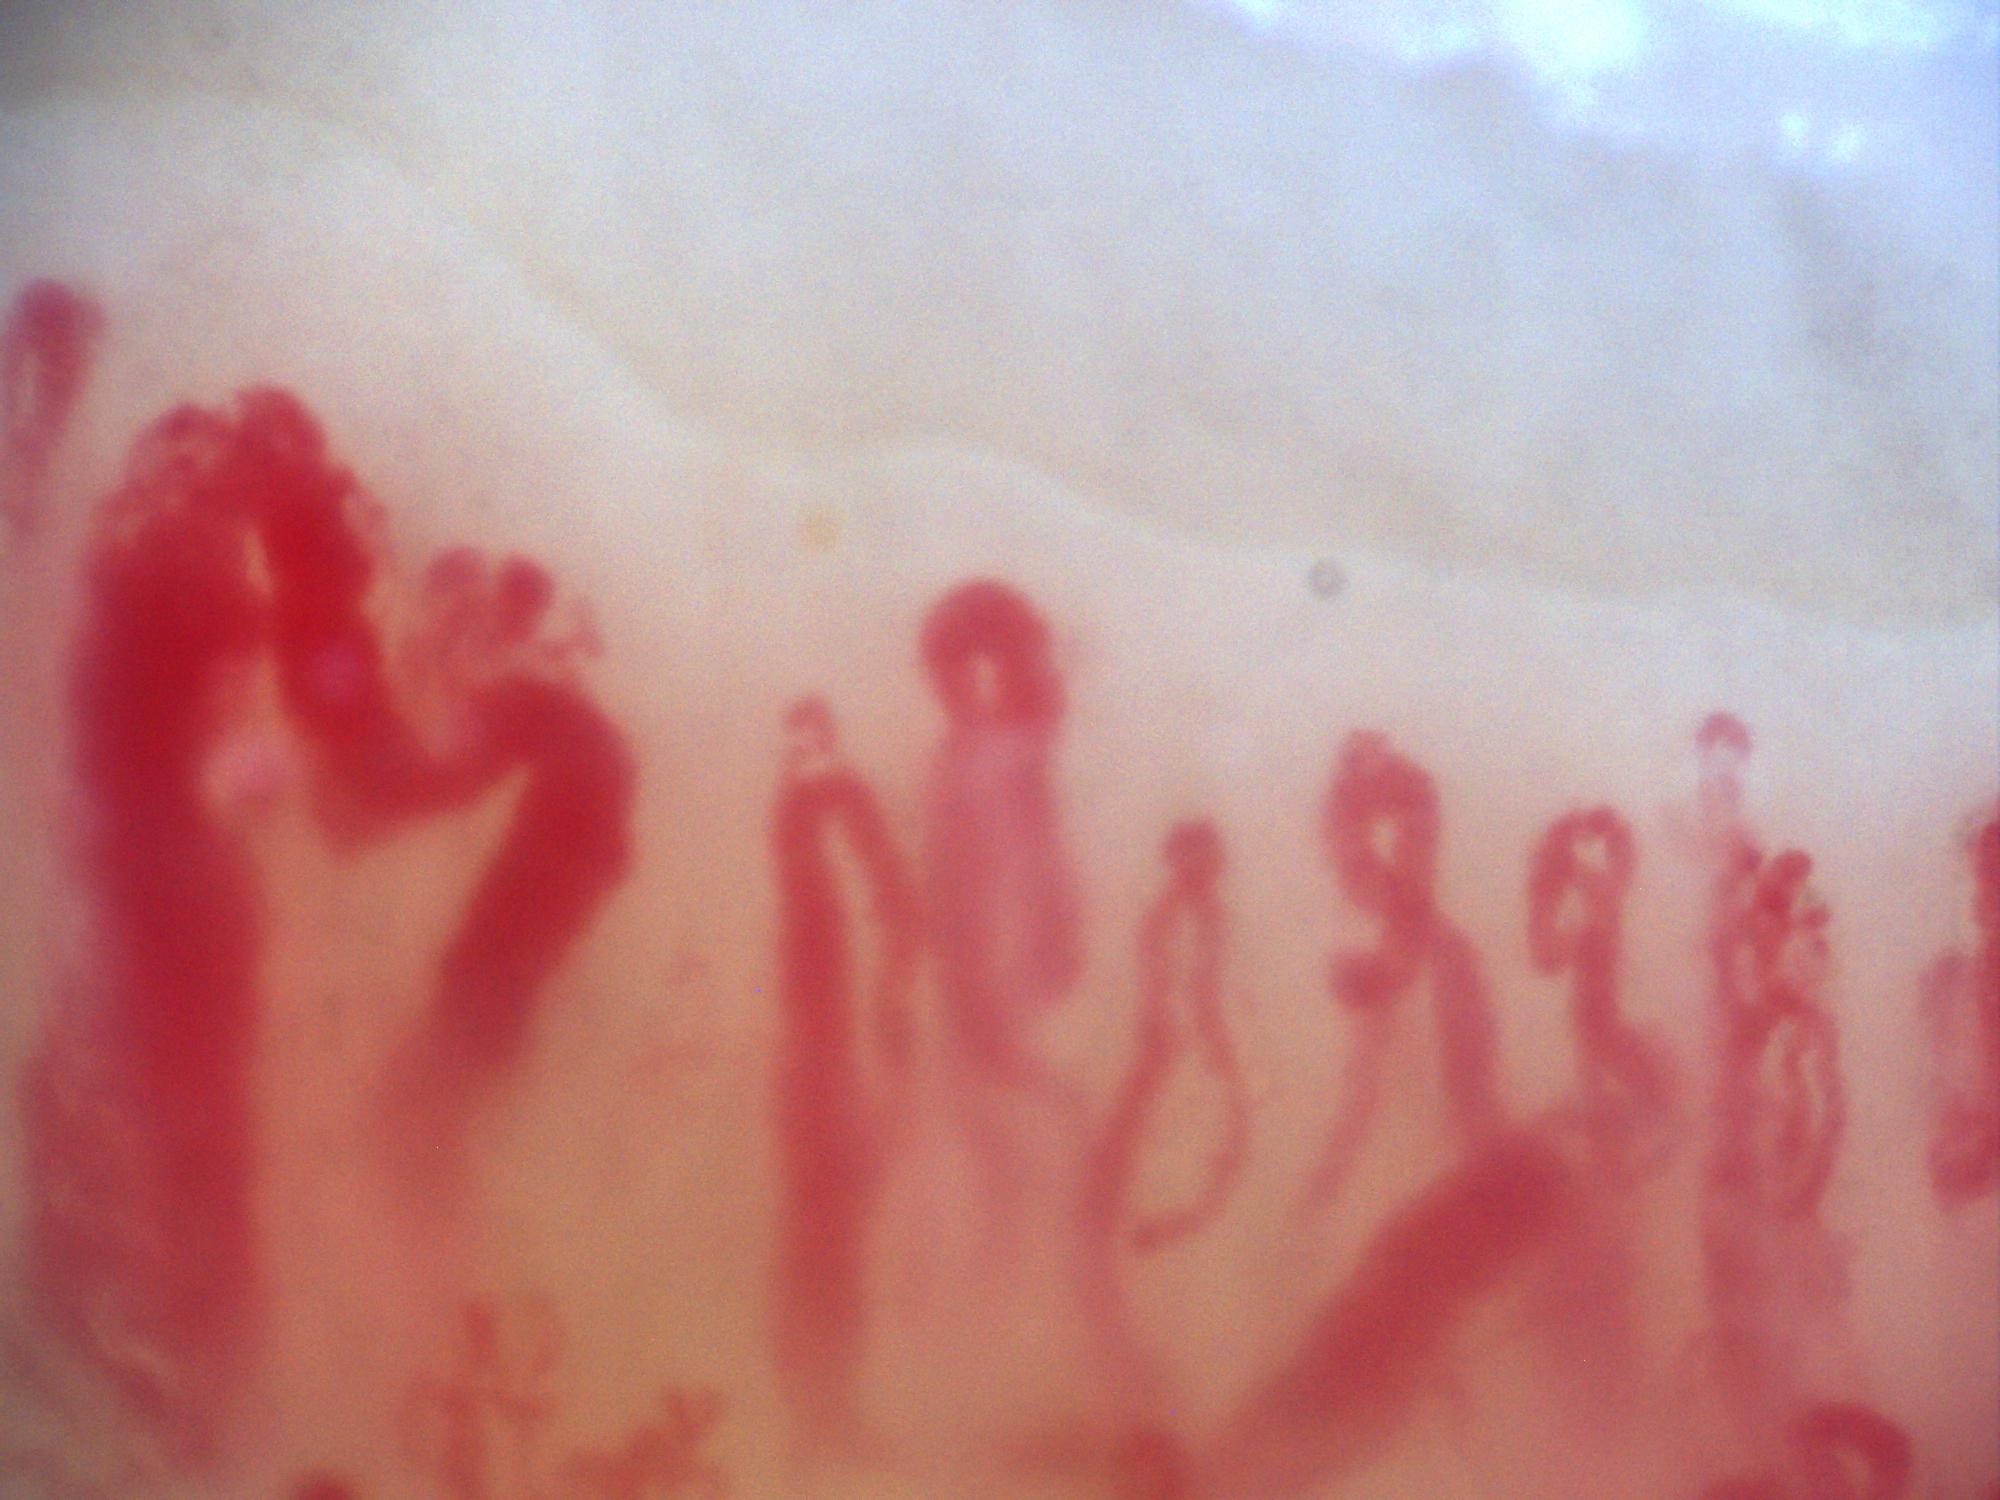
200x capillaroscopy image shared by Miguel Antonio Mesa Navas as an example of an active background with prominent megacapillaries.
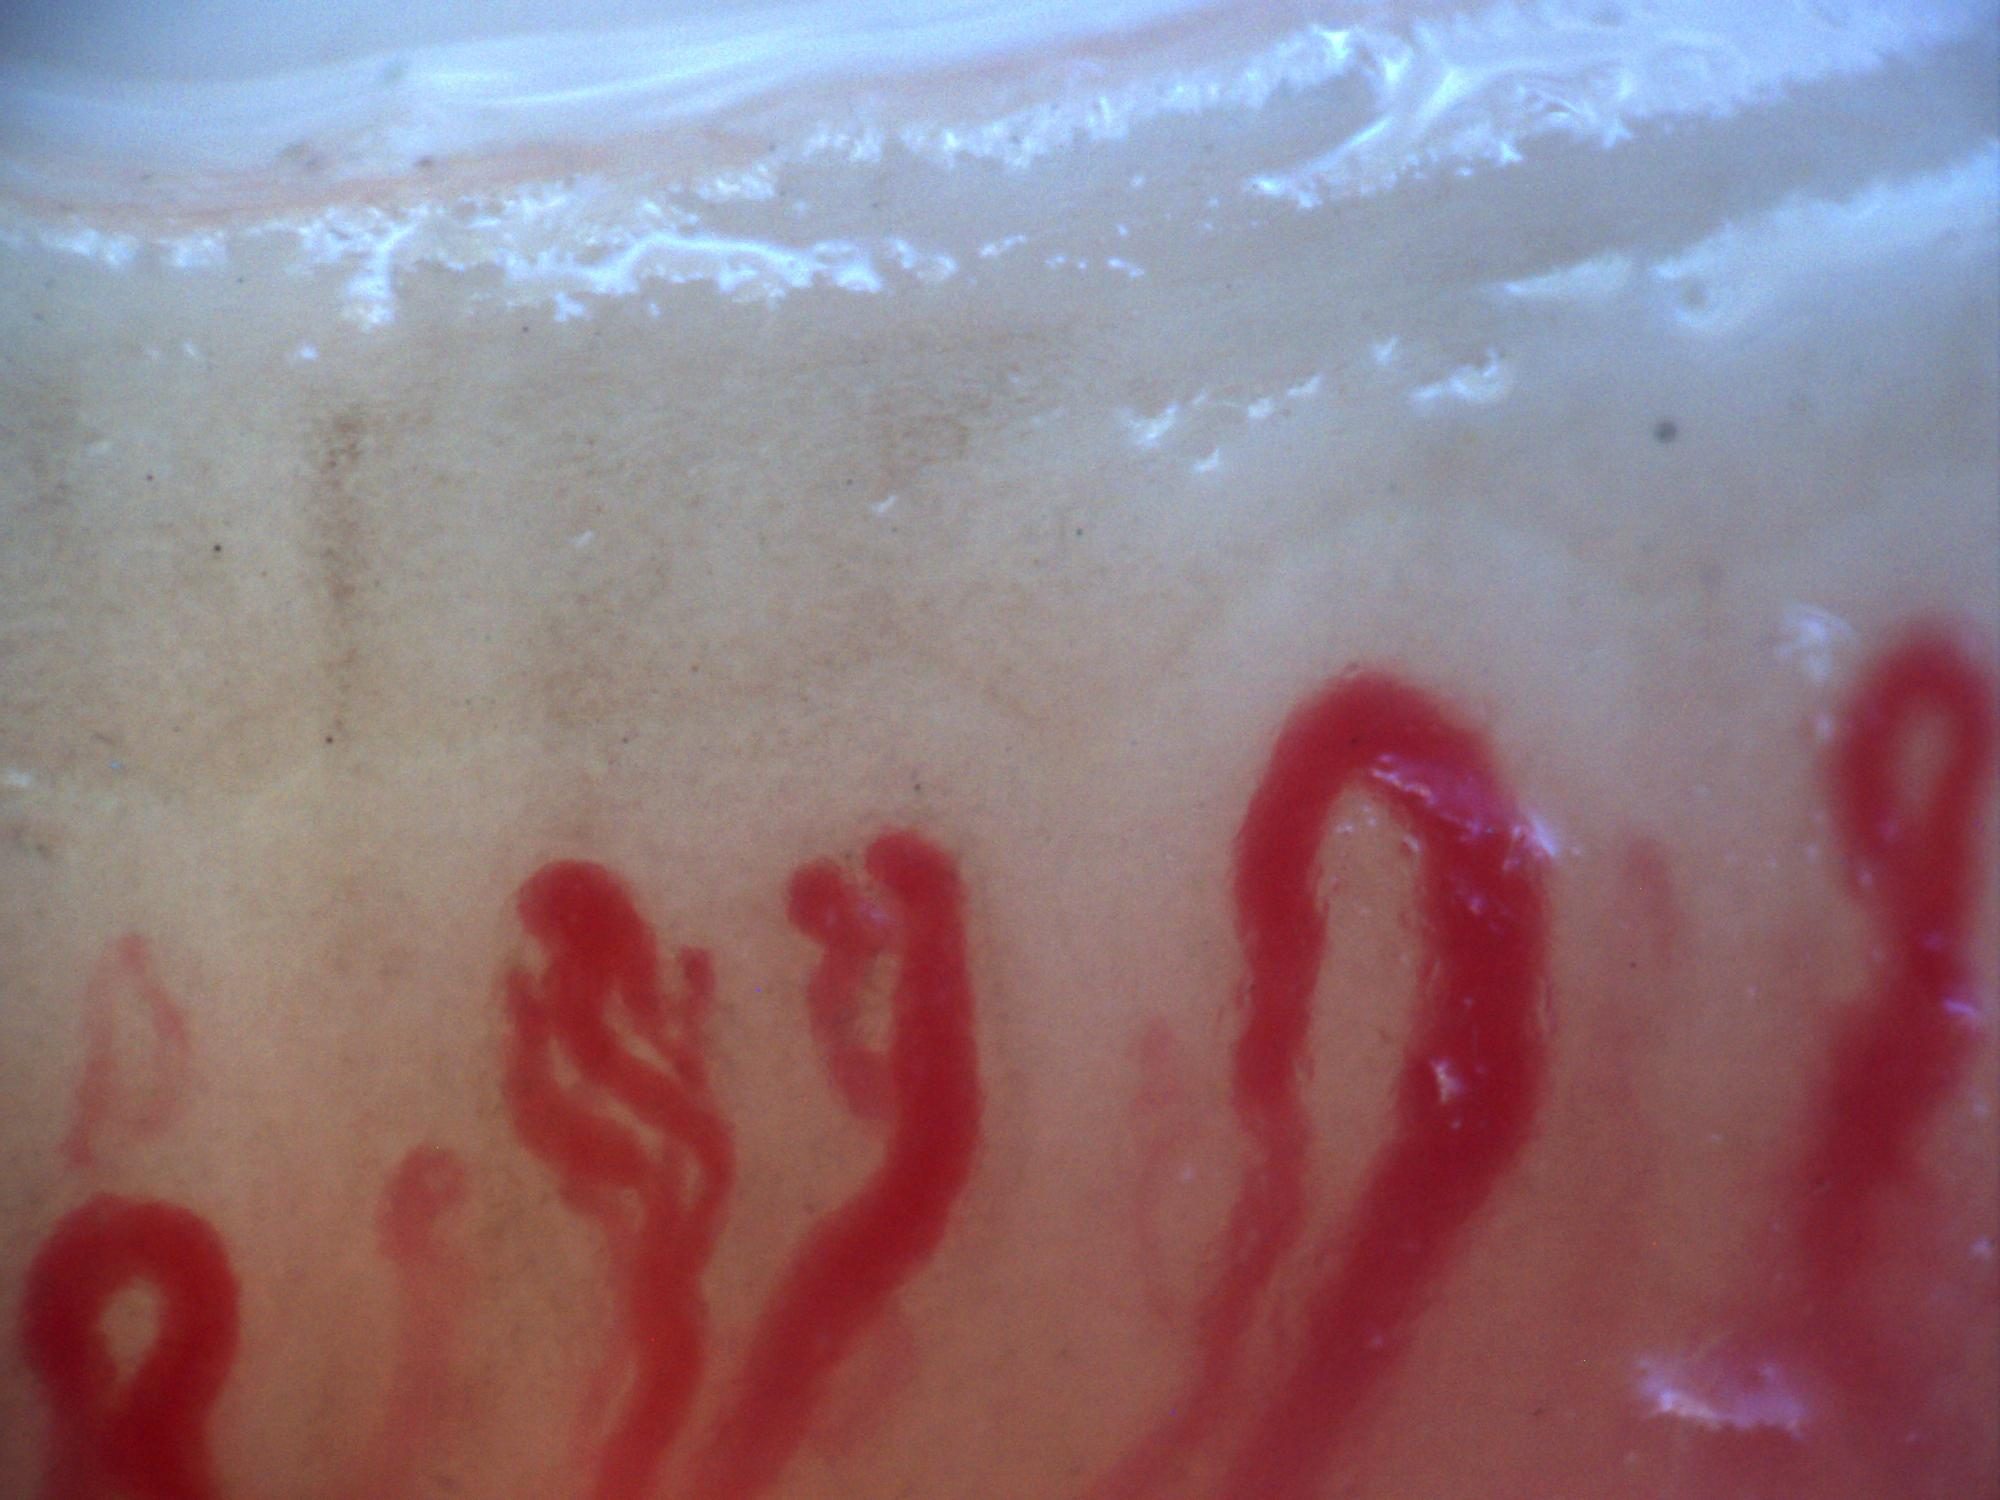
Another 200x capillaroscopy image shared by Miguel Antonio Mesa Navas as an example of an active background with prominent megacapillaries.
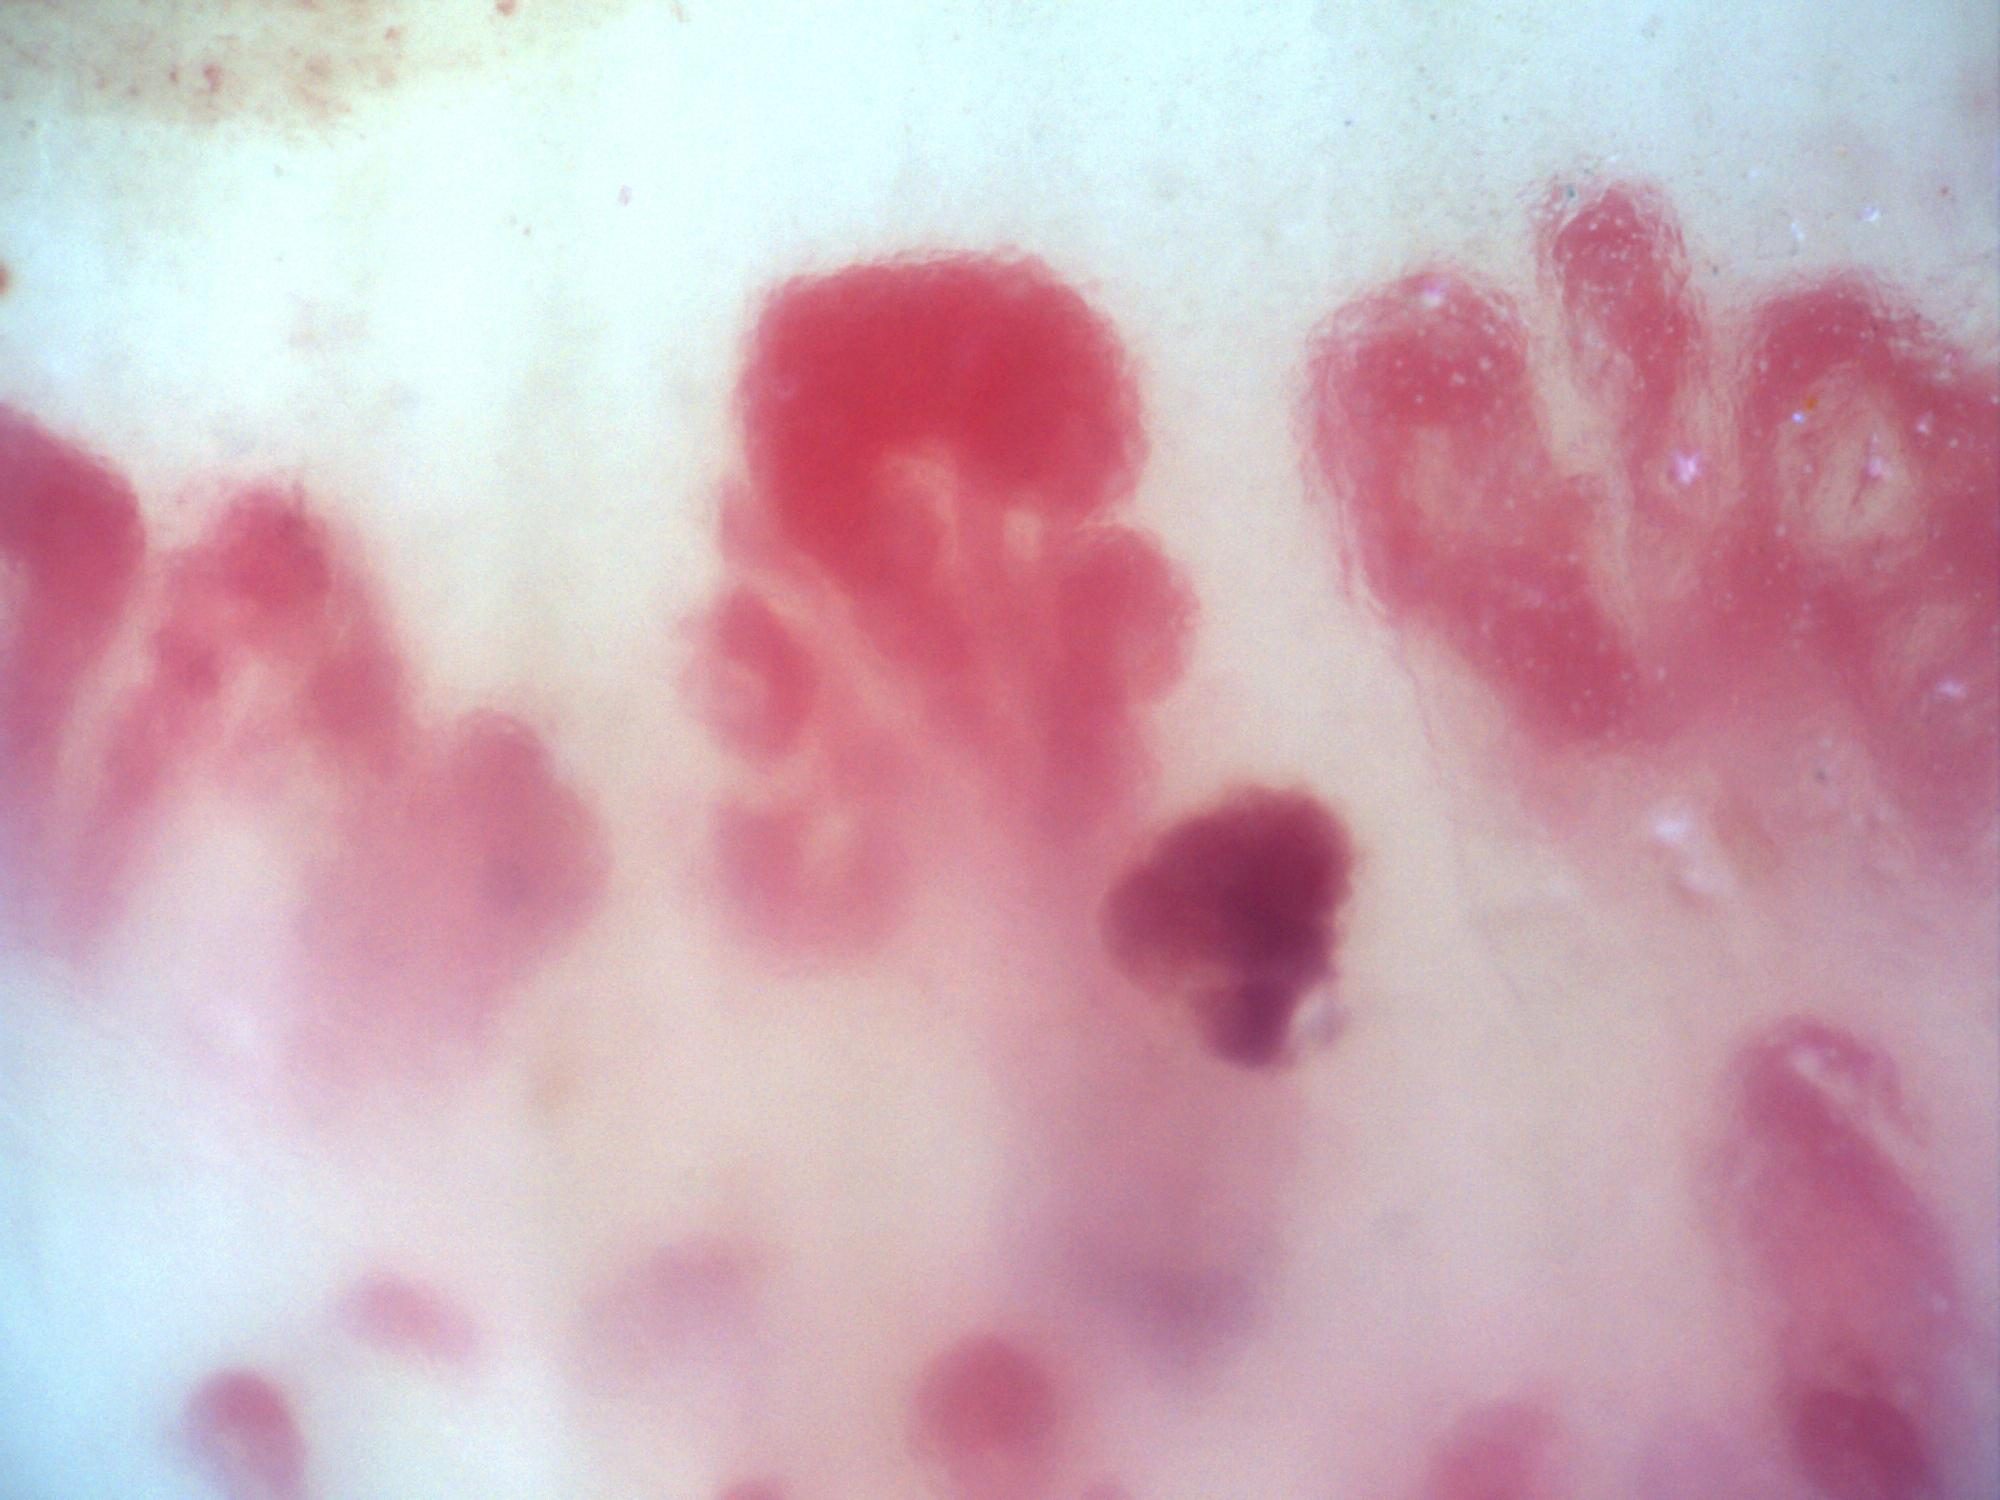
200x capillaroscopy image shared as an additional example of megacapillaries on an active background.
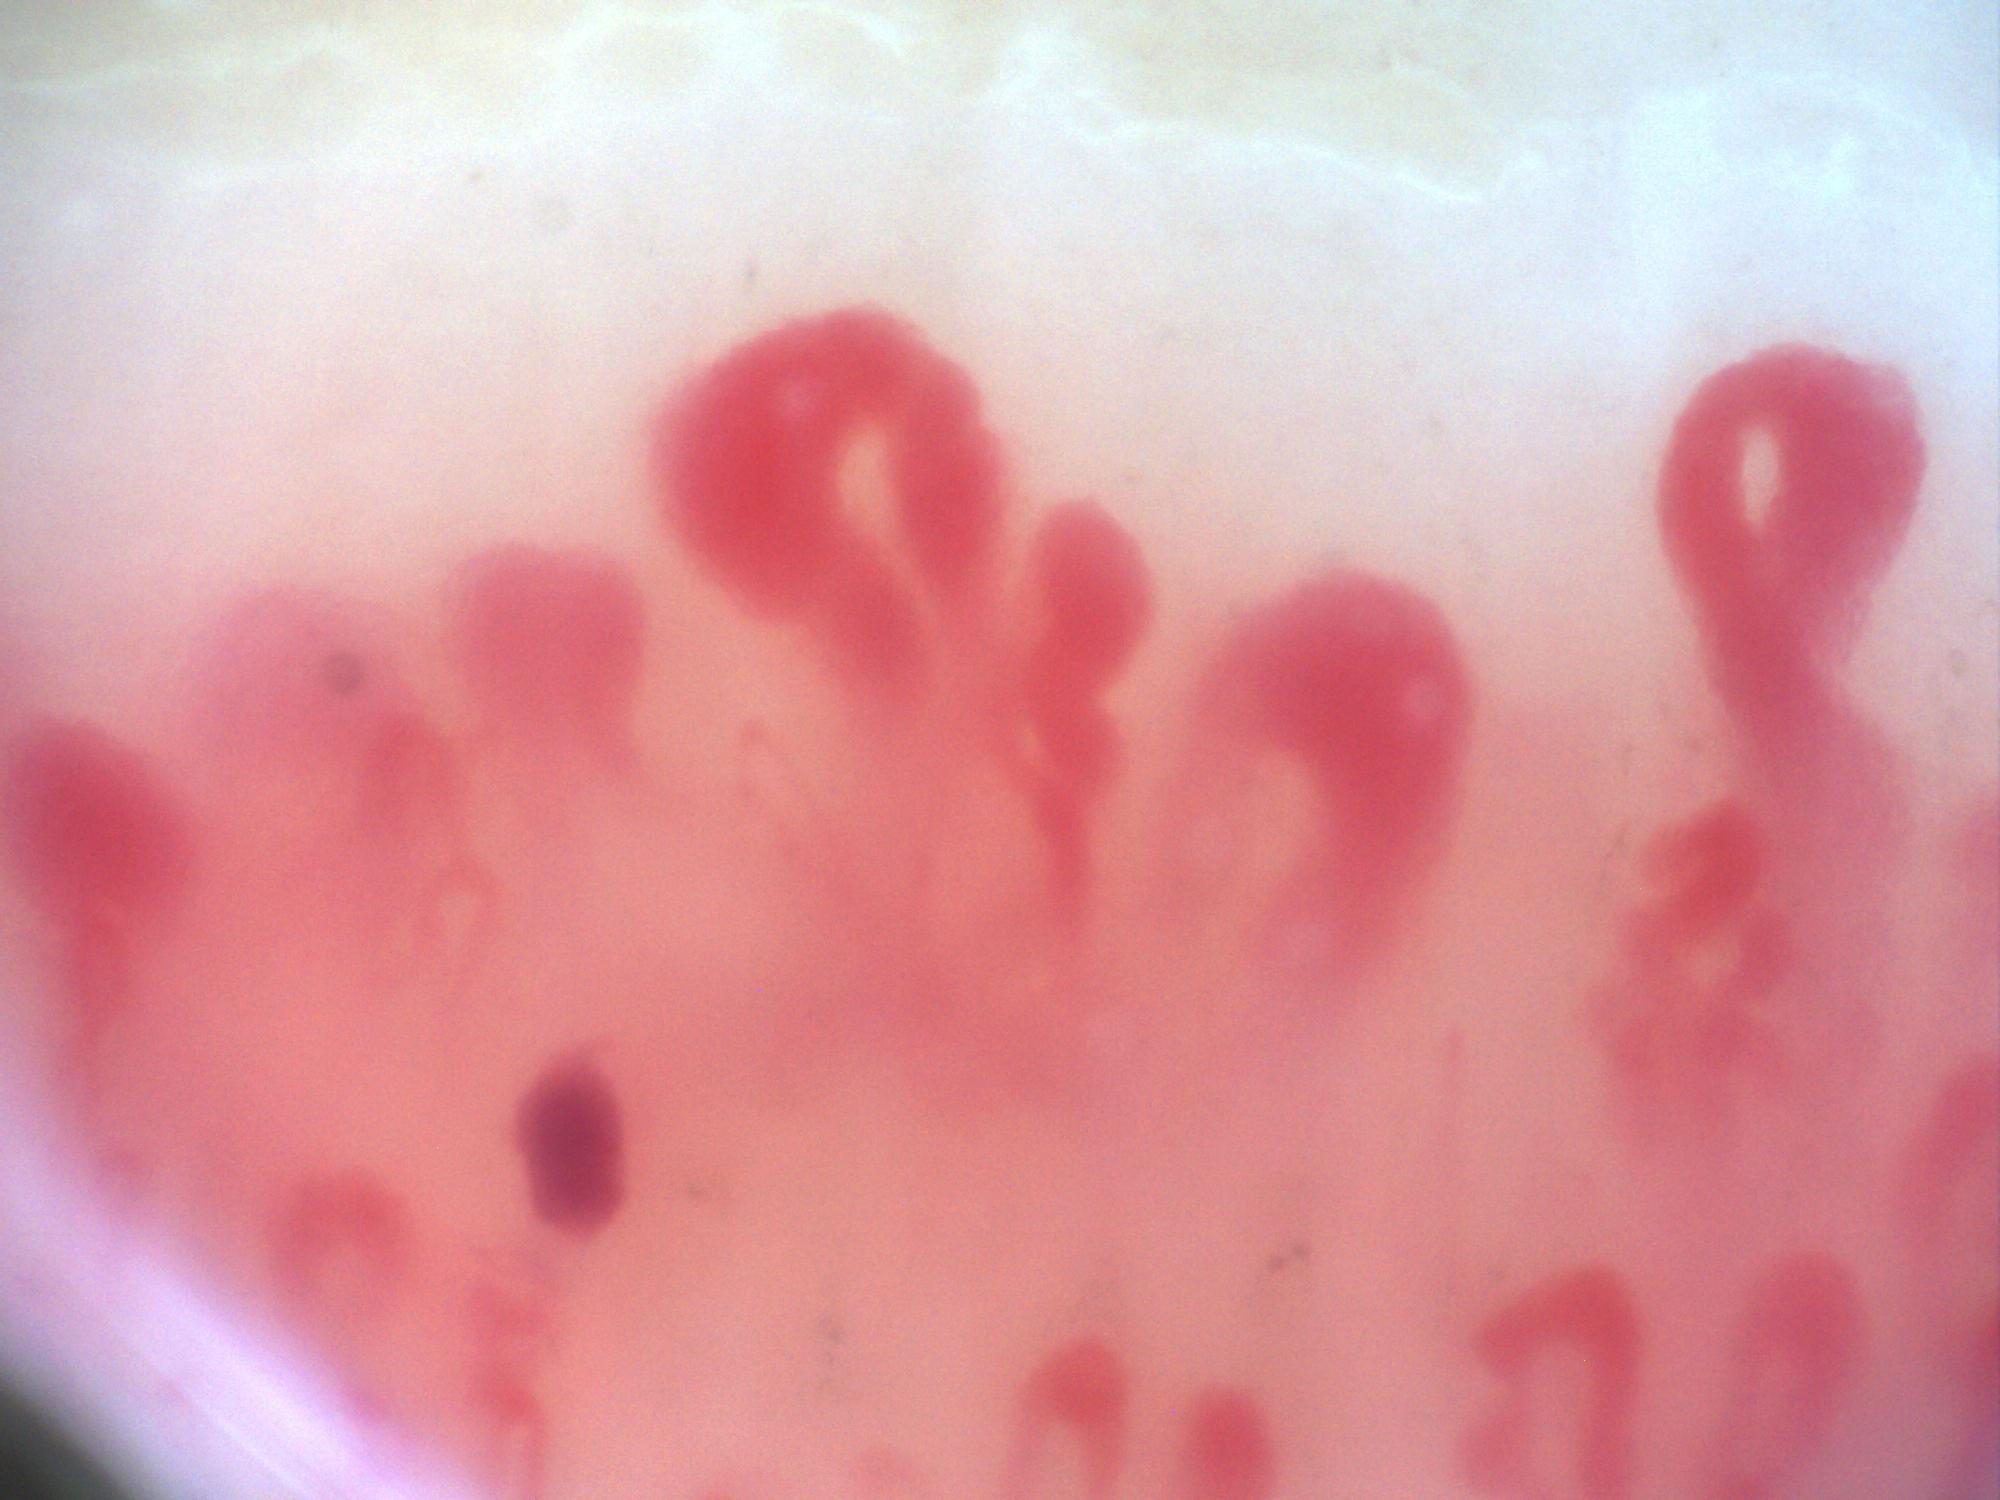
200x capillaroscopy image sent by Miguel Antonio Mesa Navas within the series of megacapillary examples.
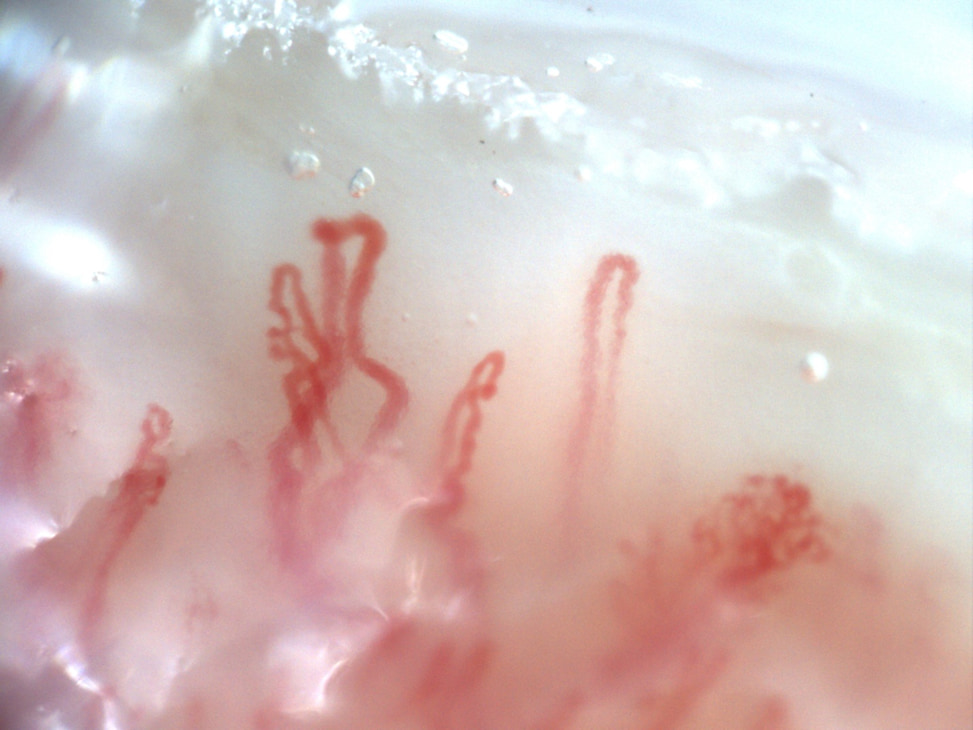 Dermatomyositis with giant and ramified capillaries
25-year-old male with anti-TIF-1γ antibody-positive dermatomyositis. Nailfold video capillaroscopy demonstrates significant microvascular architectural abnormalities characterized by enlarged and giant capillaries and multiple ramified (bushy) capillaries consistent with neoangiogenesis. No microhemorrhages are identified.
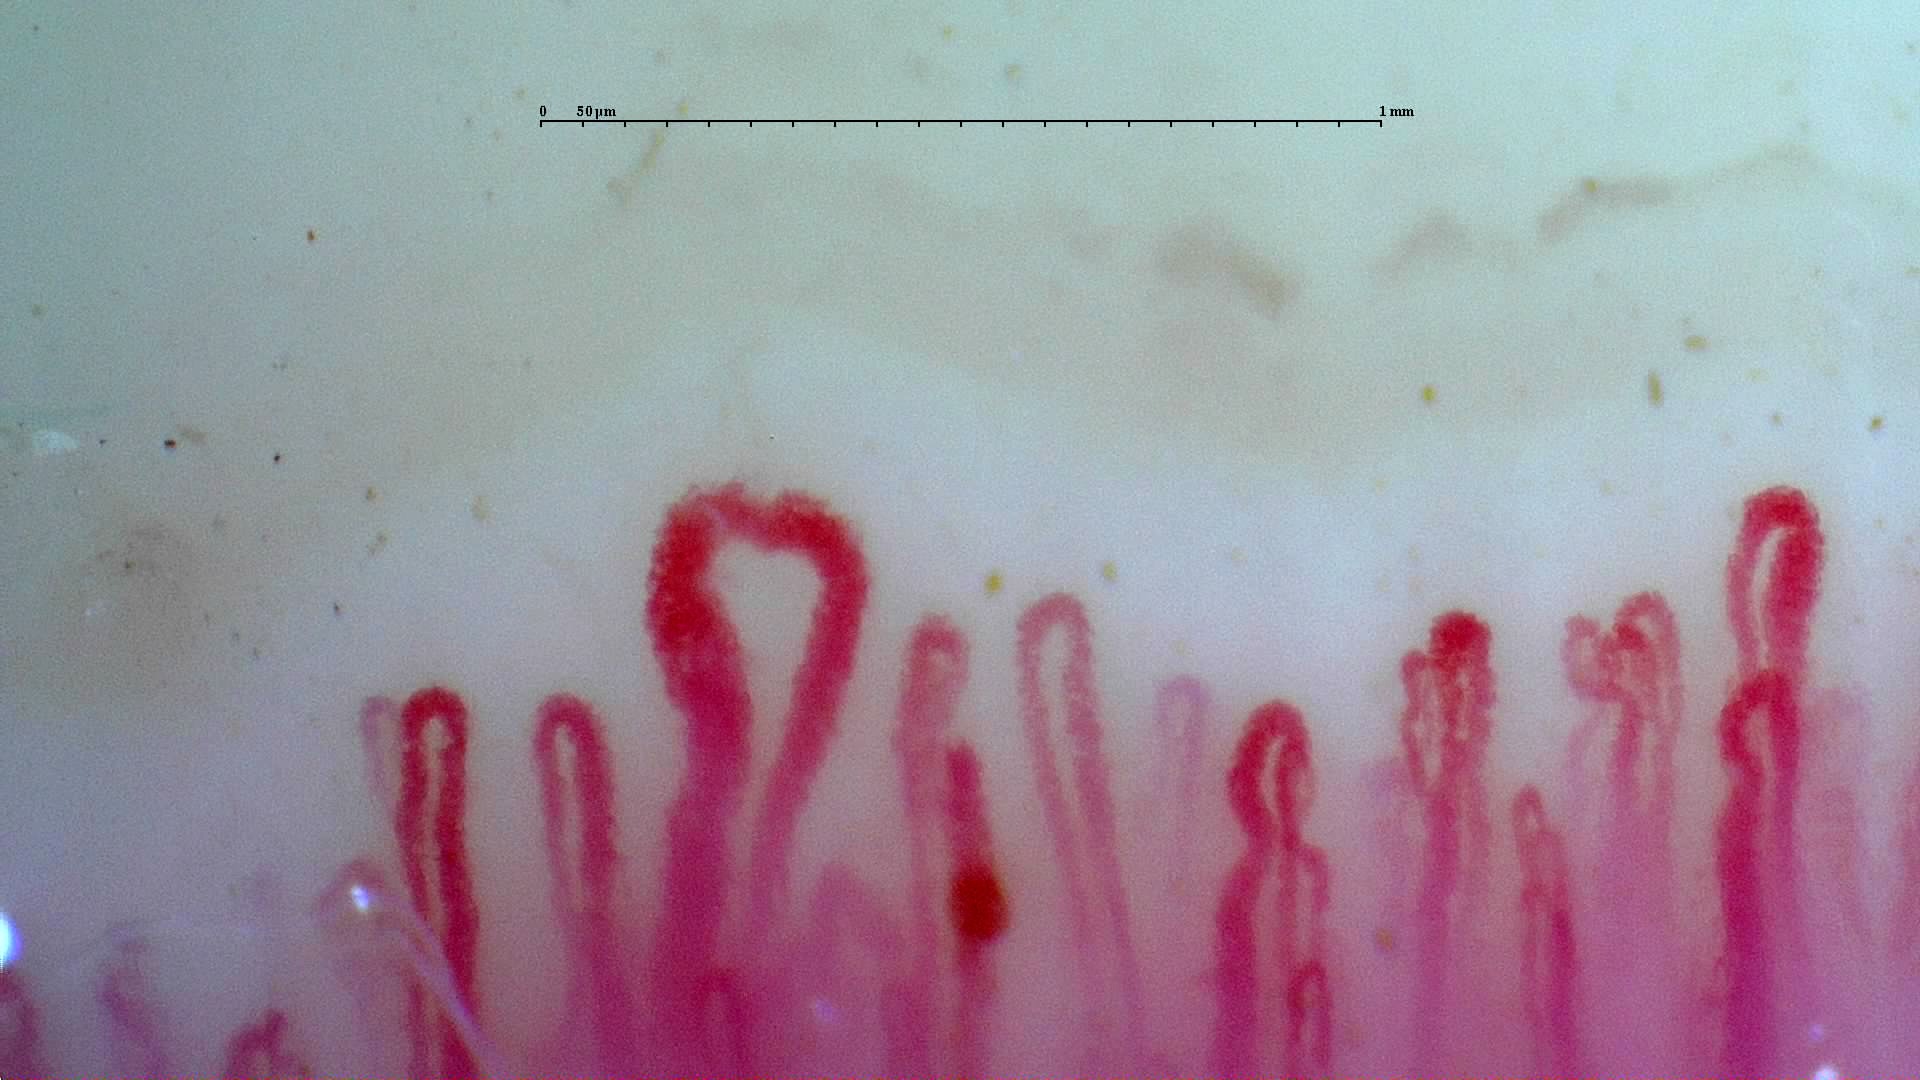 Active scleroderma pattern: giant loop
A prominent enlarged loop in the active-pattern reference study. Compare the neighboring capillaries and the other fields before assigning a pattern.
View the complete study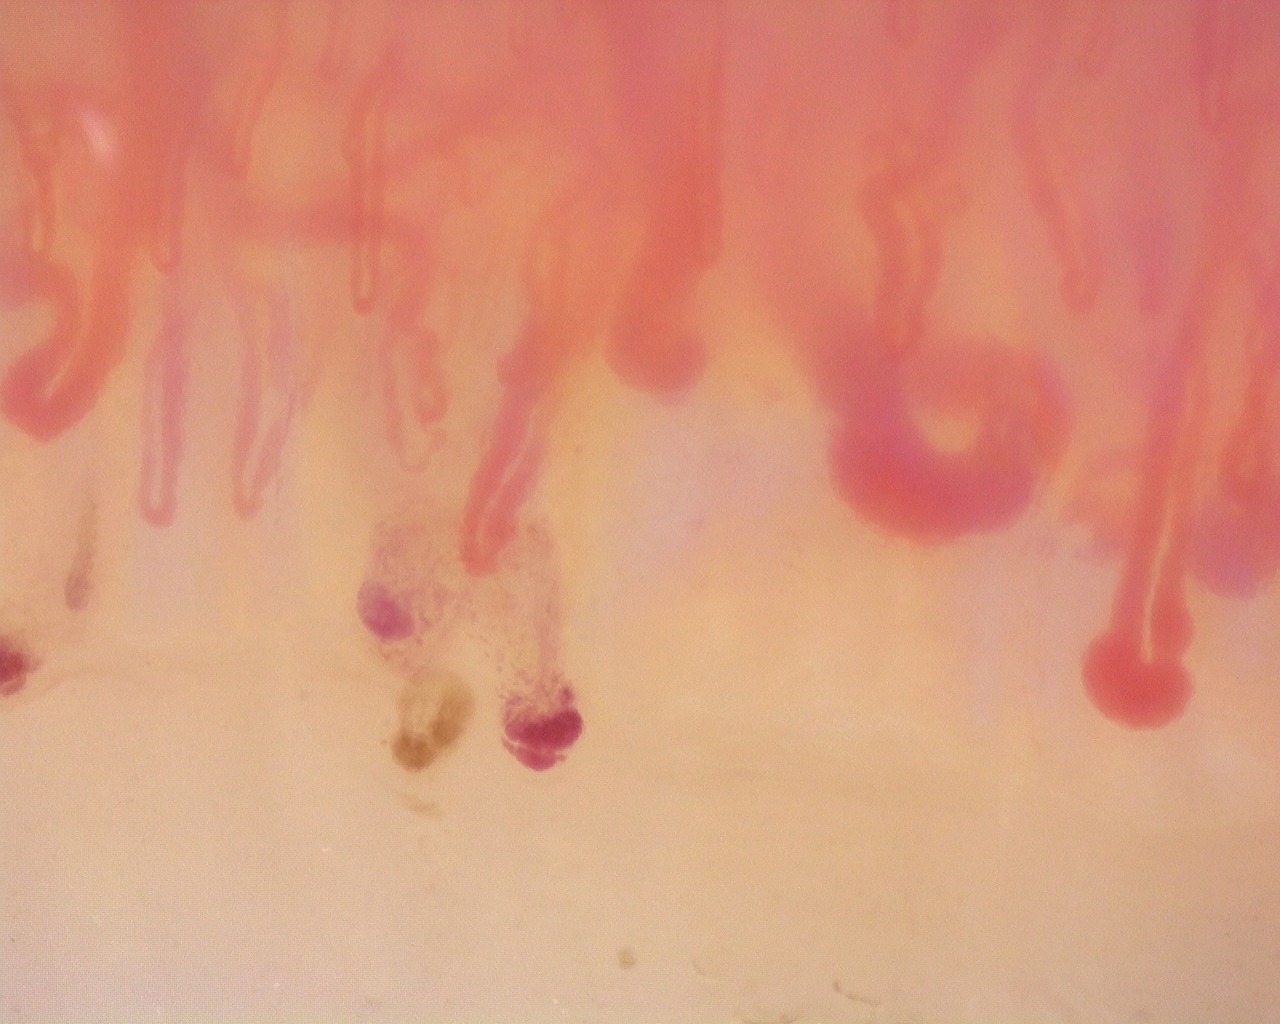 Anti-Scl-70 systemic sclerosis: enlarged loops and hemorrhages
Enlarged loops and dark hemorrhagic deposits in the anti-Scl-70-positive active-pattern case. The source report notes no avascular areas in the study.
View the complete study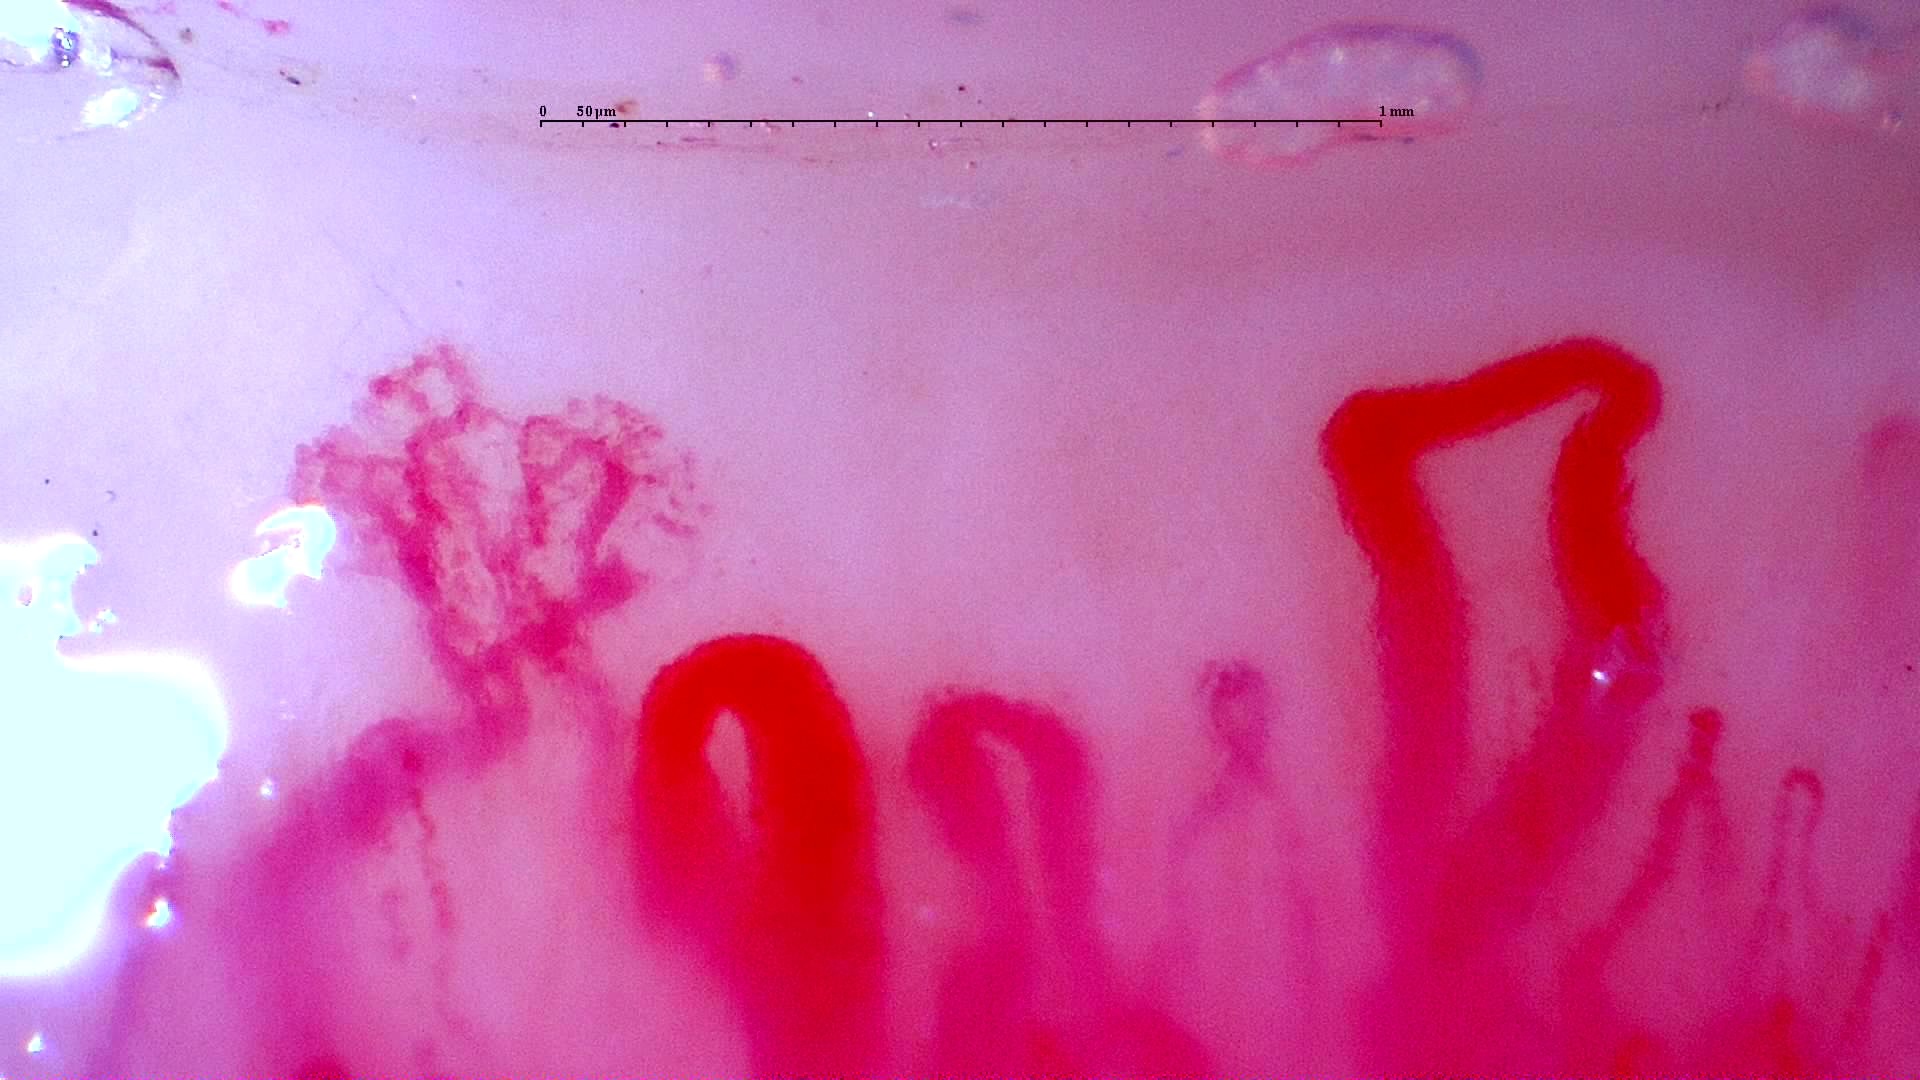 Anti-NXP2 dermatomyositis: initial enlarged loops
Prominent enlarged loops and a complex branching form in the initial anti-NXP2 dermatomyositis study. Compare this with the linked follow-up image and complete serial studies.
View the complete studyComplete cases and studies
Early SSc Cutolo Pattern: Representative Case
The study shows scattered giant capillaries and limited hemorrhages while capillary density and overall architecture remain relatively preserved.
Active SSc Cutolo Pattern: Representative Case
The study shows frequent giant capillaries and hemorrhages with reduced density and early architectural disorganization.
Limited Cutaneous Systemic Sclerosis (ACA+) with Active Cutolo Pattern
Capillaroscopy shows marked capillary loss (5.3/mm), frequent dilations, high prevalence of giant capillaries (27.5%), and hemorrhages, matching an active Cutolo pattern.
Diffuse Systemic Sclerosis (Anti-Scl-70+) with Active Cutolo Pattern
Capillaroscopy shows marked capillary reduction (5.86/mm), frequent dilations (54%), a high prevalence of giant capillaries (39.7%), and hemorrhages, without avascular areas, matching an active Cutolo pattern. The CSURI index has increased. Blood flow is homogeneous, with reduced linear velocity.
Anti-Mi2β Dermatomyositis in Active Disease
There is marked capillary loss (4.8/mm), architectural disorganization, frequent dilations, giant capillaries, and abnormal/branched shapes, indicating severe active microangiopathy.
Mixed Connective Tissue Disease with an Unclassifiable Scleroderma-Like Pattern
Capillaroscopy shows megacapillaries, but their distribution does not fit the typical organization of any early, active, or late Cutolo subtype. The overall morphology is therefore classified as a scleroderma-like pattern. Arborizing capillaries are also evident. The quantitative dataset reports a mean capillary density of 5.69/mm, enlarged capillaries in 78.7%, megacapillaries in 6.0%, and ramified forms in 4.7%.
Juvenile Dermatomyositis with Gottron Lesions and a Scleroderma-Like Pattern
The baseline capillaroscopy is compatible with juvenile dermatomyositis and shows a severe scleroderma-like microangiopathy, with marked capillary loss, frequent enlarged and giant capillaries, hemorrhages, abnormal or arborizing shapes, and architectural disorganization.
Juvenile Dermatomyositis anti-NXP2 with Capillaroscopic Improvement
The June 2024 capillaroscopy showed an early scleroderma-like pattern compatible with juvenile dermatomyositis, including reduced density, frequent enlarged capillaries, sparse giant capillaries, and hemorrhages. The December 2024 follow-up showed disappearance of giant capillaries and evolution toward a non-specific pattern, with improved capillary density.
Juvenile Dermatomyositis anti-TIF1 with Active Scleroderma-Like Pattern
Capillaroscopy shows a severe active scleroderma-like pattern, with very low capillary density, numerous giant capillaries, frequent enlarged capillaries, arborizing abnormal shapes, and architectural disorganization. This morphology is highly suggestive of active microangiopathy in juvenile dermatomyositis.
Mixed Connective Tissue Disease Presenting with Raynaud Phenomenon
The initial capillaroscopy showed an early scleroderma pattern, supporting the diagnosis in the appropriate clinical and serological context. On follow-up, clinical improvement was accompanied by improvement of capillaroscopic findings, with higher density, disappearance of giant capillaries, and evolution toward a non-specific pattern.
Anti-NXP2 Dermatomyositis with Capillaroscopic Improvement
The first study shows an active scleroderma/myositis-like microangiopathy with severe capillary loss, giant capillaries, arborizing ramifications, hemorrhages, architectural disorganization, and avascular areas. The follow-up study shows regression to a non-specific pattern with improved density and disappearance of giant capillaries and hemorrhages.
Systemic Sclerosis with anti-U3 RNP: Late Microangiopathy
There is marked capillary loss (4.9/mm), architectural disorganization, frequent dilations, giant capillaries in 14.9% of capillaries, and abnormal or ramified forms. This pattern was classified by the CAPI-Detect algorithm as active; however, due to the frequent features characteristic of late-stage involvement, it was ultimately classified as such in the final report.
References
- Smith V, et al. Standardisation of nailfold capillaroscopy for the assessment of patients with Raynaud’s phenomenon and systemic sclerosis. Autoimmun Rev. 2020;19:102458.
- Cutolo M, et al. Nailfold videocapillaroscopy assessment of microvascular damage in systemic sclerosis. J Rheumatol. 2000;27:155–160.
- Ingegnoli F, et al. Reporting items for capillaroscopy in clinical research on musculoskeletal diseases: a systematic review and international Delphi consensus. Rheumatology. 2021;60:1410–1418.
Scientific advisory board and contributors · Editorial policy